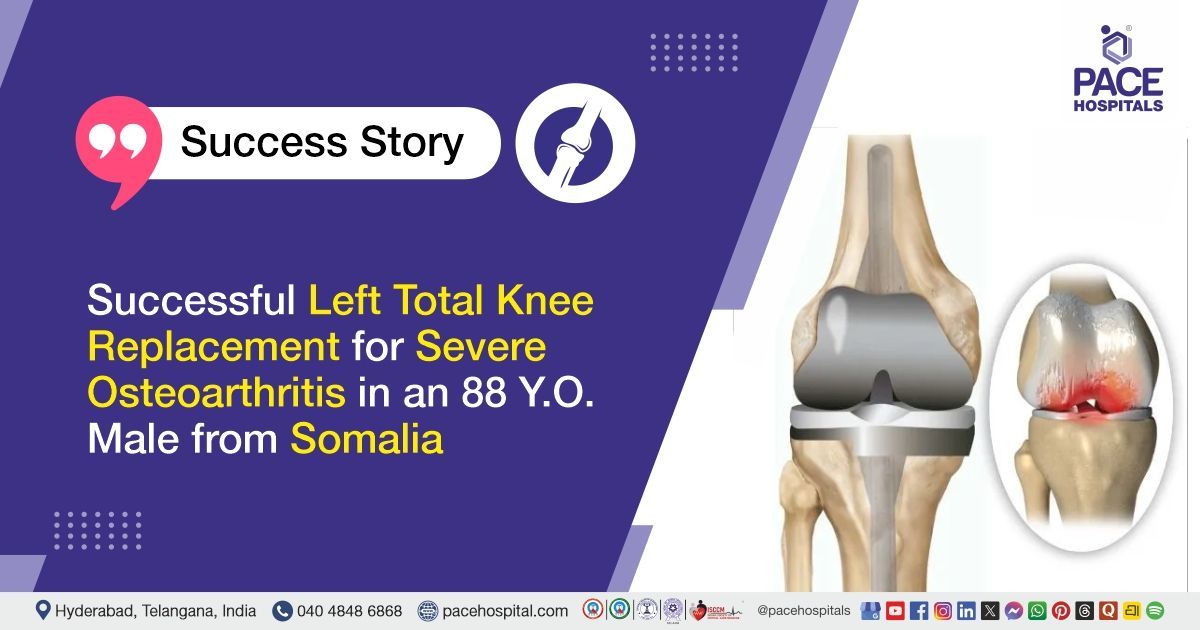
Successful Left Total Knee Replacement for Severe Osteoarthritis in an 88 Y.O. Male from Somalia
PACE Hospitals
PACE Hospitals’ expert Orthopaedic team successfully performed a Left Total Knee Replacement surgery on an 88-year-old male patient from Somalia diagnosed with severe osteoarthritis of the left knee. The procedure aimed to relieve chronic knee pain, correct the severe deformity, restore joint function, improve mobility, and enhance the patient’s overall quality of life.
Chief Complaints
An 88-year-old male patient with a body mass index (BMI) of 20 presented to the Orthopaedic Department at PACE Hospitals, Hitech City, Hyderabad, with complaints of persistent left knee pain and difficulty in fully straightening the knee for approximately one year. The restricted knee movement significantly affected his walking and daily activities. He was admitted for further evaluation and management.
Past Medical History
The patient had a history of trauma and subsequent infection involving the left lower limb approximately one year earlier, for which he underwent treatment at an outside hospital, including skin grafting.
On Examination
On examination, the patient was conscious, coherent, and oriented, with stable vital signs. Local examination of the left knee revealed a severe 90-degree flexion deformity with significant restriction of movement and associated pain. The knee was functionally compromised, affecting the patient's mobility and daily activities. There were no active clinical signs of infection in the affected limb. Systemic examination was found to be normal.
Diagnosis
Following the clinical evaluation, the Orthopaedic team at PACE Hospitals conducted a detailed assessment of the patient's persistent left knee pain and severe restriction of knee movement for approximately one year.
On examination, the patient had a 90-degree fixed flexion deformity of the left knee, with significant restriction of movement and functional limitation. An X-ray of the left knee was performed, which showed advanced degenerative changes consistent with severe osteoarthritis. The clinical and imaging findings confirmed significant joint degeneration with a severe flexion deformity.
Based on these findings, the patient was advised to undergo Osteoarthritis Treatment in Hyderabad, India, under the expert care of the Orthopaedic Department.
Medical Decision-Making (MDM)
After a detailed consultation with Dr. Raghuram (Consultant Orthopaedic Surgeon), a comprehensive evaluation was performed to determine the most appropriate treatment approach. Considering the patient's history of persistent left knee pain, severe restriction of knee movement, and difficulty performing daily activities, along with the 90-degree fixed flexion deformity, focused clinical and radiological assessments were undertaken.
Clinical examination demonstrated severe functional limitation of the left knee, while X-ray of the left knee showed advanced degenerative changes consistent with severe osteoarthritis. The significant deformity, joint degeneration, and functional impairment were considered in planning the definitive treatment.
Based on the clinical findings and imaging results, it was determined that Left Total Knee Replacement surgery was the most appropriate intervention to relieve pain, correct the severe flexion deformity, restore joint function and alignment, improve mobility, and enhance the patient's quality of life.
The patient and his family members were counselled regarding the diagnosis, proposed surgery, expected benefits, potential risks, postoperative rehabilitation, and recovery process. Informed consent was obtained before proceeding with surgery.
Surgical Procedure
Following the diagnosis and treatment decision, the patient was scheduled to undergo Left Total Knee Replacement Surgery in Hyderabad at PACE Hospitals, under the expert care of the Orthopaedic Department.
The surgical procedure involved the following steps:
- Anaesthesia, Positioning, and Surgical Preparation: The patient was administered combined spinal and epidural anaesthesia and positioned appropriately on the operating table. The left lower limb was prepared and draped under strict aseptic precautions.
- Surgical Exposure and Joint Access: A medial parapatellar approach was used to expose the left knee joint. Intraoperative assessment revealed severely porotic bone. The anterior and posterior cruciate ligaments and meniscal structures were carefully dissected and addressed to facilitate joint preparation.
- Management of Femoral and Tibial Bone: During femoral bone preparation, a hairline crack was identified and stabilised using cannulated screw fixation. The tibia was subsequently prepared with careful handling due to the underlying bone porosity.
- Correction of Flexion Deformity: To address the patient's severe 90-degree flexion deformity, posterior capsular release and pie-crusting of the iliotibial band were performed. Additional distal femoral bone cuts were made to improve alignment and achieve better correction of the deformity.
- Trial Assessment and Implant Placement: Trial components were positioned to assess joint stability, alignment, and range of motion. Following satisfactory assessment, definitive Smith & Nephew Oxinium posterior-stabilised (PS) components were implanted, including a size 6 femoral component, size 4 tibial tray with a 16 × 150 mm stem, and a 13 mm spacer.
- Closure and Completion: The operative field was thoroughly irrigated, and haemostasis was achieved. The wound was closed in layers with a surgical drain placed in situ. A sterile dressing and long-leg knee immobiliser were applied, and the patient was shifted for postoperative monitoring.
Postoperative Care
Following the left total knee replacement, the patient was closely monitored for pain, wound condition, blood loss, vital signs, and overall recovery. Postoperative care included infection prevention, pain management, blood clot prevention, and supportive treatment. Dressing and wound care were performed regularly. Physiotherapy and gait training with a walker were initiated during the hospital stay to promote early mobilisation and improve knee function.
The patient developed low haemoglobin during the postoperative period, which was managed with three units of blood transfusion. He subsequently showed satisfactory clinical recovery and was discharged in a hemodynamically stable condition.
Discharge Medications
Upon discharge, the patient was prescribed medications for infection prevention, pain and inflammation control, gastric protection, blood clot prevention, bone health, and nutritional support, along with other supportive treatment as required.
Advice on Discharge
The patient was advised to use the long-leg knee immobiliser as instructed and continue regular knee physiotherapy focusing on strengthening the quadriceps and hamstrings. Continuous passive motion (CPM) exercises with a range of 0–100 degrees were recommended to improve knee mobility. He was also advised to maintain adequate hydration, follow a balanced high-protein diet, include calcium-rich foods, and follow the rehabilitation plan provided by the Orthopaedic team.
Emergency Care
The patient was advised to contact the emergency ward at PACE Hospitals immediately in case of fever, increasing knee pain or swelling, wound redness or discharge, bleeding, sudden difficulty in walking, calf pain or swelling, breathing difficulty, or any other emergency symptoms.
Review and Follow-Up Notes
The patient was advised to return for follow-up with the Orthopaedic Doctor in Hyderabad at PACE Hospitals for wound assessment, dressing review, staple removal, evaluation of knee movement, and further rehabilitation guidance as scheduled.
Conclusion
This case highlights the successful management of severe osteoarthritis of the left knee with a 90-degree flexion deformity through left total knee replacement surgery. Despite severe deformity and porotic bone, the procedure was completed successfully with correction of the deformity and restoration of joint stability. The patient showed satisfactory postoperative recovery with physiotherapy and gait training and was discharged in a stable condition with rehabilitation and follow-up advice.
Total Knee Replacement for Severe Knee Osteoarthritis
Total knee replacement is an established treatment for severe knee osteoarthritis when pain, stiffness, deformity, and restricted mobility significantly affect daily activities and conservative treatments do not provide adequate relief. The procedure involves removing damaged joint surfaces and replacing them with artificial components to relieve pain, restore knee alignment, and improve joint function.
Careful preoperative assessment, including clinical evaluation and knee imaging, helps determine the severity of joint damage and suitability for surgery. Appropriate implant selection, accurate bone preparation, and proper alignment are important for achieving stable and durable results. After surgery, early mobilisation, physiotherapy, pain management, and blood-clot prevention support recovery. Regular follow-up with an Orthopaedic Doctor/Orthopaedic Surgeon helps monitor healing, knee function, implant performance, and long-term outcomes.
Frequently Asked Questions (FAQs)
What is severe osteoarthritis of the knee?
Severe knee osteoarthritis occurs when the cartilage that cushions the knee joint becomes significantly worn down. This can cause persistent pain, stiffness, swelling, grinding sensations, deformity, and difficulty walking or performing everyday activities. In advanced cases, the joint may become severely damaged and movement can be markedly restricted.
When is total knee replacement recommended for osteoarthritis?
Total knee replacement is generally considered when severe osteoarthritis causes persistent pain, significant stiffness or deformity, and difficulty with walking or daily activities, especially when treatments such as medicines, physiotherapy, weight management, and injections have not provided adequate relief. The decision is based on symptoms, examination findings, imaging, overall health, and functional limitations.
Can a severe knee flexion deformity be corrected with total knee replacement?
Yes, in appropriately selected patients, total knee replacement can help correct a significant fixed flexion deformity. During surgery, the damaged bone and tissues are carefully addressed, and appropriate bone cuts and soft-tissue releases may be performed to improve knee alignment and extension. The degree of correction depends on the severity and individual condition of the knee.
How does total knee replacement improve walking and mobility?
During total knee replacement, damaged joint surfaces are replaced with artificial components that provide a smoother and more stable joint surface. This can reduce pain, improve alignment and movement, and make activities such as standing and walking easier. Physiotherapy after surgery further helps restore strength, balance, and mobility.
What are the possible complications of total knee replacement?
Possible complications include infection, bleeding, blood clots, stiffness, persistent pain, nerve or blood-vessel injury, implant loosening or wear, and problems with knee movement. Most patients recover without major complications when appropriate surgical care, postoperative monitoring, and rehabilitation are followed.
How soon can a patient walk after total knee replacement?
Many patients are encouraged to begin standing and walking with assistance, often within the first day or two after surgery, depending on their medical condition and surgical recovery. A walker or other support may initially be needed. Mobility is gradually increased under the guidance of the physiotherapy team.
Why is physiotherapy important after knee replacement surgery?
Physiotherapy helps reduce stiffness, restore knee movement, strengthen the muscles around the joint, improve balance, and support a safe return to walking and daily activities. Following the prescribed rehabilitation programme is an important part of achieving good long-term functional recovery.
What exercises are recommended after total knee replacement?
Exercises commonly include ankle pumps, quadriceps and hamstring strengthening, straight-leg raises, knee-bending and straightening exercises, and walking or gait training. The exact exercises and their intensity should be determined by the orthopaedic and physiotherapy teams based on the patient's recovery.
What is continuous passive motion (CPM) after knee replacement?
Continuous passive motion (CPM) is a device that gently moves the knee through a controlled range of motion without requiring the patient to actively move the joint. It may be used in selected patients to support early knee movement, although its routine use varies depending on the patient's condition and the treating team's rehabilitation protocol.
When can a patient return to normal daily activities after knee replacement?
Recovery varies from person to person. Many patients gradually resume routine activities over several weeks, while full functional recovery can take several months. Activities should be increased progressively according to pain, strength, knee movement, and the advice of the orthopaedic and physiotherapy teams.
Share on
Request an appointment
Fill in the appointment form or call us instantly to book a confirmed appointment with our super specialist at 04048486868
Appointment request - health articles
Recent Articles