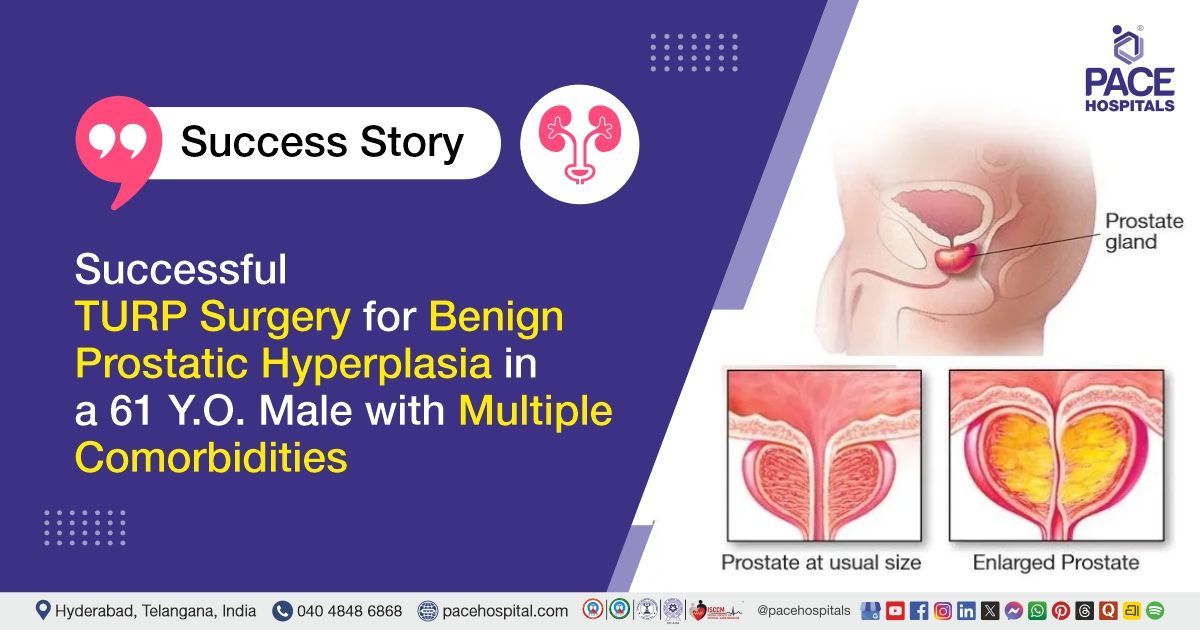
Successful TURP Surgery for Benign Prostatic Hyperplasia in a 61 Y.O. Male with Multiple Comorbidities
PACE Hospitals
PACE Hospitals’ Urology team successfully performed a Transurethral Resection of the Prostate (TURP) on a 61-year-old male patient diagnosed with benign prostatic hyperplasia (BPH). The procedure aimed to remove the obstructing prostate tissue, restore urinary flow, relieve urinary retention and lower urinary tract symptoms, improve bladder emptying, and support the patient’s overall quality of life.
Chief Complaints
A 61-year-old male patient with a
body mass index (BMI) of 21 presented to the Urology Department at
PACE Hospitals, Hitech City, Hyderabad, with complaints of poor urine flow and acute urinary retention (AUR) requiring urinary catheterisation. His urinary symptoms had progressed to the point where he was unable to empty his bladder adequately, prompting further evaluation and management.
Past Medical History
The patient was a known case of
coronary artery disease (CAD), diabetes mellitus,
hypertension,
dyslipidemia, and
hypothyroidism. He was on regular medications for his existing medical conditions. He also had a history of multidrug-resistant organism (MDRO) infection, which was managed based on antibiotic susceptibility testing.
On Examination
On examination, the patient was conscious, coherent, and oriented, with stable vital signs. He was noted to have acute urinary retention with a Foley catheter in situ. General and systemic examination was performed as part of his preoperative assessment. His
cardiovascular, respiratory, abdominal, and neurological status was evaluated, particularly considering his underlying CAD,
diabetes, hypertension, and other comorbidities.
Diagnosis
Upon admission to PACE Hospitals, following a detailed clinical assessment, the Urology team evaluated the patient for poor urine flow and acute urinary retention.
The patient underwent a comprehensive diagnostic workup, including complete blood picture, urine examination, renal function assessment, serum electrolytes, liver function tests, coagulation profile, blood sugar testing, blood grouping, viral screening, and other preoperative investigations. These evaluations were performed to assess his overall medical condition and fitness for surgical intervention.
Based on the patient's clinical presentation and investigations, he was diagnosed with benign prostatic enlargement (BPE) associated with acute urinary retention. Benign prostatic enlargement is a non-cancerous increase in prostate size that can narrow the urinary passage and interfere with normal urine flow. In advanced cases, it may result in difficulty passing urine or complete urinary retention requiring catheterisation.
The patient also had coronary artery disease, diabetes mellitus, hypertension, dyslipidemia, and hypothyroidism, which were considered during preoperative assessment and optimisation. His blood glucose levels were monitored and controlled with insulin, and his multidrug-resistant infection was managed according to antibiotic susceptibility results.
Based on the confirmed diagnosis and clinical assessment, the patient was advised to undergo
Benign Prostatic Enlargement Treatment under the supervision of the Urology Department.
Medical Decision Making (MDM)
After a detailed consultation with Dr. Abhik Debnath (Consultant Laparoscopic Urologist), a comprehensive evaluation was performed to determine the most appropriate treatment approach for the patient presenting with poor urine flow and acute urinary retention requiring catheterisation.
Considering the patient's benign prostatic enlargement, urinary obstruction, acute urinary retention, and associated medical conditions including coronary artery disease, diabetes mellitus, hypertension, dyslipidemia, and hypothyroidism, a thorough preoperative assessment was undertaken. His blood sugar was poorly controlled, with an HbA1c of 9.6% and random blood glucose levels ranging from 300–500 mg/dL, and was therefore optimised with insulin therapy before surgery.
The patient also had a multidrug-resistant organism (MDRO) infection. Antibiotic treatment was administered based on the susceptibility results. His regular antiplatelet therapy was stopped 5 days before surgery to reduce the risk of bleeding, as clinically appropriate.
Following the necessary investigations, medical optimisation, and pre-anaesthetic assessment, it was determined that Transurethral Resection of the Prostate (TURP) under spinal anaesthesia was the appropriate treatment strategy. The procedure was planned to remove the obstructing prostate tissue, improve urinary flow, relieve bladder outlet obstruction, and reduce dependence on urinary catheterisation.
The patient and his family members were counselled regarding the diagnosis, planned procedure, anaesthesia, potential risks and benefits, expected postoperative recovery, catheter care, medication management, and the importance of follow-up.
Surgical Procedure
Following the decision, the patient was scheduled for Transurethral Resection of the Prostate (TURP) in Hyderabad at PACE Hospitals, under the supervision of the Urology Department.
The following steps were carried out during the procedure:
- Patient Preparation and Anaesthesia: After obtaining informed consent and completing the pre-anaesthetic evaluation, the patient was taken to the operating room. Standard aseptic precautions were maintained, and spinal anaesthesia was administered. The patient was positioned appropriately for the procedure.
- Insertion of the Resectoscope: A specialised endoscopic instrument called a resectoscope was introduced through the urinary opening and advanced through the urethra to reach the prostate. The procedure was performed without any external surgical incision.
- Identification of the Obstructing Prostate Tissue: The enlarged prostate tissue responsible for the bladder outlet obstruction was identified. The obstructing tissue was assessed carefully before resection.
- Resection of Prostate Tissue: The obstructing prostate tissue was gradually removed using an electrical cutting loop. The resected tissue was collected and sent for histopathological examination as appropriate.
- Control of Bleeding: Bleeding points within the resected area were carefully controlled to achieve adequate haemostasis and reduce the risk of postoperative bleeding.
- Catheter Placement and Completion: A Foley urinary catheter was placed to facilitate urine drainage following the procedure. The procedure was completed successfully without intraoperative complications, and the patient was shifted to the postoperative recovery area in a stable condition.
Postoperative Care
The patient had an uneventful postoperative recovery and remained hemodynamically stable throughout the hospital stay. He was closely monitored for urine output, urinary bleeding, pain, hydration status, blood sugar levels, and overall recovery, considering his underlying medical conditions. Appropriate treatment was provided to prevent infection, relieve pain and discomfort, protect the stomach, prevent constipation, and support recovery. The Foley catheter remained in place at the time of discharge, and the patient was advised to return for follow-up and catheter removal after 5 days.
Discharge Medications
Upon discharge, the patient was prescribed medicines to prevent postoperative infection, relieve pain, control fever when required, protect the stomach from medication-related irritation, facilitate urinary symptoms, and prevent constipation. His regular medicines for diabetes, blood pressure, cholesterol, and thyroid disease were continued as advised. He was also instructed to resume antiplatelet therapy after 3 weeks, as recommended by the treating team.
Advice on Discharge
The patient was advised to maintain adequate hydration, with approximately 2 litres of fluid per day, and follow a diabetic-friendly, balanced diet.
Catheter-care instructions were provided while the Foley catheter remained in place. After catheter removal, scheduled voiding, double voiding, and pelvic floor exercises were to be introduced as advised by the treating team.
He was instructed to avoid tea, coffee, spicy foods, weightlifting, forward bending, straining during bowel movements, and prolonged travel by bus, auto, or two-wheeler during the initial recovery period. Mild suprapubic discomfort, occasional blood or cloudy urine, or mild burning during urination may occur temporarily and generally improve within 7–10 days.
Emergency Care
The patient was advised to contact the emergency ward at PACE Hospitals in case of any emergency or development of symptoms such as fever, severe pain, vomiting, difficulty passing urine, reduced urine output, heavy bleeding, blood clots in the urine, dizziness, or worsening urinary symptoms.
Review and Follow-up Notes
The patient was advised to return for a follow-up visit with the Urologist after 5 days.
Conclusion
This case highlights the successful management of benign prostatic enlargement with acute urinary retention using Transurethral Resection of the Prostate (TURP). The procedure was completed without complications, and the patient was discharged in a stable condition with the Foley catheter in situ. Appropriate postoperative care, adequate hydration, Kegel exercises, scheduled voiding, double voiding, and regular follow-up were advised to support recovery and improve bladder control.
Medical Disclaimer: This information is for general educational purposes only and does not replace consultation with a qualified urologist. Treatment decisions and recovery after TURP vary depending on the severity of urinary obstruction, prostate size, bladder function, overall health, comorbidities, infection status, medications, and other individual clinical factors.
Optimizing Recovery After TURP in Patients with Benign
Prostatic Enlargement and Acute Urinary Retention
Transurethral Resection of the Prostate (TURP) is an established treatment for men with benign prostatic enlargement causing significant urinary obstruction and acute urinary retention. By removing the prostate tissue responsible for blocking the urinary passage, TURP can improve urine flow and reduce dependence on a urinary catheter. Careful preoperative optimisation is particularly important in patients with conditions such as diabetes, coronary artery disease, hypertension, dyslipidemia, and hypothyroidism. After surgery, adequate hydration, scheduled voiding, double voiding, pelvic floor exercises when advised, appropriate activity restrictions, and regular follow-up with a
urologist/urology doctor can support bladder recovery and improve long-term urinary function.
Frequently asked questions (FAQs)
Can an enlarged prostate cause acute urinary retention?
Yes, an enlarged prostate can press on the urethra and obstruct the normal flow of urine from the bladder. In some men, the blockage can become severe enough to suddenly prevent urination, which results in acute urinary retention and the need for a urinary catheter.
When is TURP recommended for benign prostatic enlargement?
TURP may be recommended when an enlarged prostate causes significant urinary problems that do not improve adequately with medicines, or when complications such as repeated urinary retention occur. It may also be considered when the obstruction significantly affects bladder emptying or causes other urinary complications.
How does TURP improve urine flow?
During TURP, the urologist removes the portion of prostate tissue that is blocking the urethra. This creates more space for urine to pass from the bladder, which can improve urinary flow and make bladder emptying easier.
How long does a catheter stay after TURP?
The catheter is left in place after TURP to allow urine to drain while the surgical site heals, and it also helps to monitor urine output and bleeding. The exact duration varies depending on the patient's recovery. In some patients, it may be removed within a few days, while in others it may need to be left in longer.
Is blood in the urine normal after TURP?
A small amount of blood in the urine can be common during the early recovery period because the prostate has been surgically treated. The urine generally becomes clearer as healing progresses. Heavy bleeding, large blood clots, or difficulty passing urine should be reported to a doctor promptly.
Can urinary symptoms continue after the TURP procedure?
Yes. Some patients may temporarily experience urinary frequency, urgency, a mild burning sensation, or changes in urinary control after TURP. These symptoms usually improve as the urinary passage and bladder recover. Persistent or worsening symptoms should be evaluated by the urologist.
What is double voiding and how does it help after TURP?
Double voiding means urinating normally, waiting for a short time, and then trying to urinate again. This can help empty any urine that remains in the bladder after the first attempt. It may be useful during recovery in patients who have difficulty completely emptying their bladder.
Why are Kegel exercises recommended after TURP?
Kegel exercises strengthen the pelvic floor muscles that help control urine. They may help improve bladder control and reduce temporary urine leakage or dribbling after prostate surgery. Patients should perform them using the technique and schedule recommended by their urologist.
Can an enlarged prostate cause kidney problems?
Yes, an enlarged prostate can cause kidney problems. When the prostate grows, it blocks the flow of urine. This blockage traps urine in the bladder, creating back pressure that can damage or fail the kidneys over time if left untreated.
When should a patient seek emergency care after TURP?
A patient should seek immediate medical attention for inability to pass urine, heavy or persistent bleeding, large blood clots, severe or worsening pain, fever, repeated vomiting, markedly reduced urine output, dizziness, or other rapidly worsening symptoms. These symptoms may indicate a complication requiring prompt assessment.
Share on
Request an appointment
Fill in the appointment form or call us instantly to book a confirmed appointment with our super specialist at 04048486868
Appointment request - health articles
Recent Articles